Porcelain Veneer Cementation Protocol: 7 Proven Steps by Dr. Ali Cem ULUBEY
Quick answer: Porcelain veneer cementation is the bonding step that fixes each veneer to the tooth, and its quality strongly affects how long the veneer lasts. At Ulubey Dental Clinic in Antalya, Dr. Ali Cem Ulubey and Dr. Surur Ulubey follow a 7-step adhesive protocol: preserve enamel, etch e.max with hydrofluoric acid for 20 seconds, apply silane, sandblast and prime zirconia, preview the cement shade with try-in pastes, light-cure each surface and clean the margins. E.max veneers carry a 5-year clinic guarantee against fracture or debonding, conditional on attending the recommended check-ups.
Executing a meticulous porcelain veneer cementation protocol is the critical bridge connecting exquisite laboratory ceramic artistry with long-term clinical retention. A veneer is only as durable as its adhesive resin interface; even the most lifelike lithium disilicate restoration will fail prematurely if surface conditioning, bonding chemistry, or curing physics are compromised.
In modern aesthetic dentistry, whether restoring smiles through porcelain veneers in Antalya or comprehensive digital smile design transformations, treating cementation as a simple “gluing step” is a major clinical error. This guide outlines the 7 proven clinical steps of our adhesive protocol at Ulubey Dental Clinic, designed to maximize micromechanical bond strength and prevent post-operative thermal sensitivity.
Quantitative parameters of our porcelain veneer cementation protocol, grounded in peer-reviewed adhesive literature (Blatz, Magne, Pashley), Ivoclar’s instructions for use and clinical practice:
- Step 1: Substrate Biology — Enamel Conservation vs. Dentin Tubules
- Step 2: Glass-Ceramic Etching — The 20-Second e.max Standard
- Step 3: Chemical Silanization & The Condensation Reaction
- Step 4: Polycrystalline Zirconia Conditioning — 10-MDP Coordination
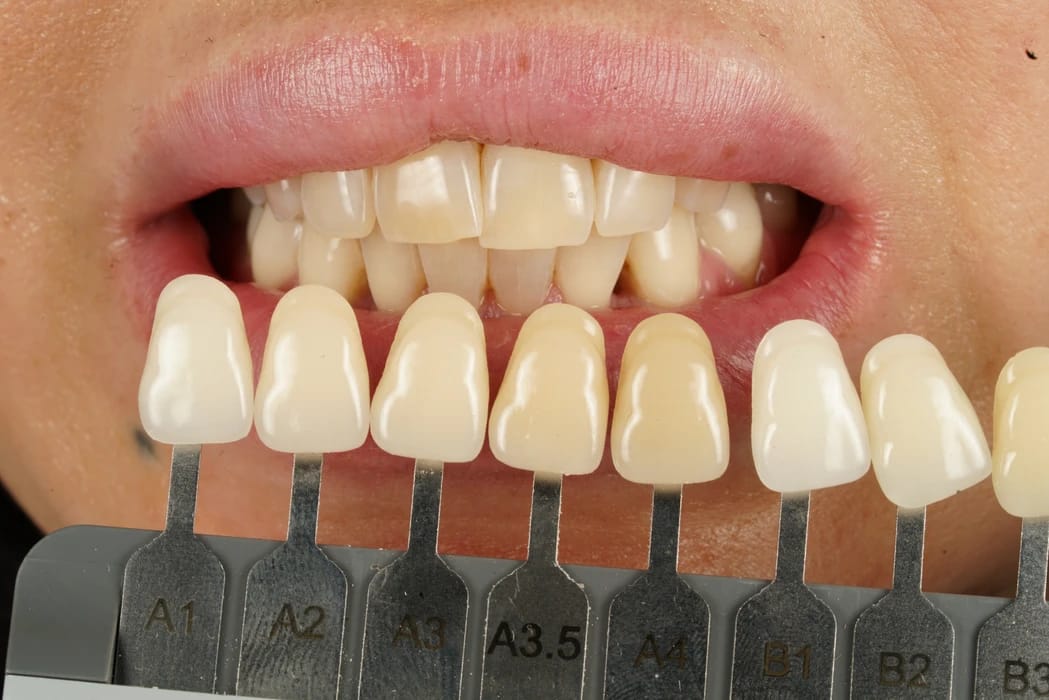
- Step 5: Optical Shade Calibration with Try-In Pastes
- Step 6: Photopolymerization Physics via Collimated LED
- Step 7: Marginal Clean-Up & Biological Width Preservation
- Clinical FAQs: Sensitivity, Materials & Longevity
- Peer-Reviewed Biomimetic Literature Citations

Step 1: Substrate Biology — Enamel Conservation vs. Dentin Tubules
The biological substrate dictates the predictable longevity of any porcelain veneer cementation protocol. Human dental enamel consists of 96% hydroxyapatite mineral crystals organized in microscopic prisms. When etched with 37% orthophosphoric acid (H₃PO₄) for 15 to 30 seconds, enamel dissolves into a honeycombed micro-retentive surface, creating reliable micromechanical retention: in a prospective 10-year clinical trial, none of 87 bonded porcelain veneers was lost (Peumans et al., 2004).
Dentin, however, is a vital, hydrated tissue containing 70% mineral, 20% organic collagen matrix, and 10% water. Dentin is traversed by thousands of microscopic dentinal tubules (20,000 to 45,000 per mm²) filled with outward-flowing dentinal fluid under positive pulpal pressure.
When aggressive tooth reduction cuts deep into dentin, hydrodynamic fluid movement inside exposed tubules triggers sensory nerve fibers (A-delta fibers) within the dental pulp. If the hybrid layer is not sealed properly during cementation, masticatory flexure creates microscopic fluid shifts, resulting in chronic, sharp pain when drinking cold water or chewing.
Step 2: Glass-Ceramic Etching — The 20-Second IPS e.max Standard
Lithium disilicate glass-ceramics (Ivoclar IPS e.max) rely on a silica-rich glassy matrix embedded with interlocking lithium disilicate crystals (Li₂Si₂O₅). To create a micro-porous retention pattern, the ceramic intaglio must be conditioned with Hydrofluoric Acid (HF):
- Etching Time per Manufacturer: an etching gel with under 5% hydrofluoric acid (IPS Ceramic Etching Gel) is applied for 20 seconds on IPS e.max Press and CAD, as specified in Ivoclar’s instructions for use; a longer reaction time does not improve the bond (on resin bonding to ceramics, see also Blatz et al., 2018).
- The Risk of Over-Etching: Leaving HF acid on lithium disilicate for 60 seconds dissolves the crystal framework excessively, precipitating insoluble fluorosilicate salts that can weaken the ceramic and the bond.
- Post-Etch Ultrasonic Neutralization: After thorough water rinsing, the restoration is submerged in an ultrasonic bath of 96% isopropyl alcohol or neutralizer for 3 minutes to dissolve residual acid salts.
Step 3: Chemical Silanization & The Condensation Reaction
Acid etching creates mechanical micro-undercuts, but durable adhesion requires a true chemical covalent bond. This is achieved using a Silane Coupling Agent (typically 3-methacryloxypropyltrimethoxysilane):
• Ceramic-Si-OH: Hydrolyzed hydroxyl groups on the etched porcelain glass surface.
• HO-Si-R: Hydrolyzed silanol groups of the silane coupling molecule.
• Si-O-Si (Siloxane Bridge): High-energy chemical covalent bond linking porcelain to the resin matrix.
• Warm Air Activation: Warm air-drying (45°C) evaporates residual water and alcohol, accelerating the condensation reaction.
Step 4: Polycrystalline Zirconia Conditioning — 10-MDP Coordination
A critical rule in dental biomaterials: Hydrofluoric acid has no etching effect on zirconia. Polycrystalline zirconia (3Y, 4Y, or 5Y-TZP zirconia) contains no silica glass phase; applying HF acid to zirconia simply contaminates the surface.
| Material Class | Surface Etching Chemical | Chemical Primer | Bonding Mechanism |
|---|---|---|---|
| IPS e.max (Lithium Disilicate) | Hydrofluoric acid gel, under 5% (20 seconds) | Silane Coupling Agent (MPS) | Micromechanical retention + Siloxane covalent bonds (Si-O-Si). |
| Feldspathic Veneers | 9% Hydrofluoric Acid (60–90 seconds) | Silane Coupling Agent (MPS) | High-porosity micromechanical retention + Siloxane coupling. |
| Monolithic Zirconia (4Y/5Y-TZP) | Air-abrasion (50 µm Al₂O₃, 1.5–2.0 bar) | 10-MDP Monomer | Micro-roughened surface + Phosphate-to-zirconium chemical coordination (P-O-Zr). |
To condition zirconia for adhesive luting, the surface must be gently air-abraded with 50 µm aluminum oxide particles at low pressure (1.5 to 2.0 bar) to create mechanical roughness without inducing tetragonal-to-monoclinic phase transformation. Next, a primer containing the functional monomer 10-Methacryloyloxydecyl dihydrogen phosphate (10-MDP) is applied. The dihydrogen phosphate group forms a direct chemical coordination bond with zirconium dioxide atoms (P-O-Zr), yielding durable adhesion.
Step 5: Optical Shade Calibration with Try-In Pastes
Because ultra-thin cosmetic veneers (0.3 to 0.5 mm) possess natural optical translucency, the final tooth shade is a triad combination of:
- The underlying prepared tooth structure (stump shade / ND value),
- The ceramic ingot opacity and vitality (reviewed in our clinical tooth shade guide),
- The optical color and opacity of the adhesive resin cement.
At Ulubey Dental Clinic, Dr. Surur Ulubey evaluates the aesthetic outcome before bonding using glycerine-based, water-soluble Try-in pastes (Warm, Neutral, Light, and Bleach). These pastes match the refractive index of fully polymerized resin cement, allowing patient and doctor to preview the true shade under 5500K daylight illumination before irreversible light-curing.
Considering veneers yourself? See our veneers treatment page and our smile design options.
Step 6: Photopolymerization Physics via Collimated LED
Incomplete curing of luting resin is a primary cause of veneer failure, margin darkening, and pulp toxicity. Light emitted from standard LED curing wands diverges rapidly; by the time photons penetrate through a 0.5 mm porcelain veneer and reach the underlying resin, irradiance can drop by 50% to 70%.
At Ulubey Dental Clinic, our porcelain veneer cementation protocol relies on the Dentsply Sirona SmartLite Pro modular LED system. Featuring a custom optical lens assembly, the SmartLite Pro produces an ultra-uniform, collimated light beam delivering over 1,200 mW/cm² of active irradiance. This ensures high monomer-to-polymer conversion rates through porcelain, sealing dentin margins and preventing fluid micro-leakage.
Step 7: Marginal Clean-Up & Biological Width Preservation
Residual hardened cement flash at the subgingival margin is a frequent cause of chronic gum inflammation and redness after cosmetic treatment. In our protocol:
-
Tack-Curing & Flash Removal
The veneer is seated with passive finger pressure. A 1-to-2 second wave of light cures the resin cement to a gel state, allowing excess cement to be cleanly peeled away in one piece with a sharp scaler without chipping the margin.
-
Oxygen Inhibition Layer Management
Before final light-curing, margins are coated with an air-barrier glycerine gel. This prevents ambient oxygen from inhibiting the superficial 10–20 µm of resin, ensuring maximum surface hardness at the margin.
-
Definitive Circumferential Polymerization
Each surface (facial, incisal, palatal) is polymerized for a full 40 seconds with the SmartLite Pro LED system.
-
Occlusal Calibration & Canine Guidance
Centric stops and lateral excursions are verified with 8 µm articulation foil. Premature shearing contacts in lateral guidance are relieved to protect porcelain from fracture.
Clinical FAQs: Sensitivity, Materials & Longevity
Peer-Reviewed Biomimetic Literature Citations
- Blatz, M. B., Sadan, A., & Kern, M. (2003). Resin-ceramic bonding: a review of the literature. Journal of Prosthetic Dentistry, 89(3), 268–274.
- Blatz, M. B., Vonderheide, M., & Conejo, J. (2018). The effect of resin bonding on long-term success of high-strength ceramics. Journal of Dental Research, 97(2), 132–139.
- Peumans, M., et al. (2004). A prospective ten-year clinical trial of porcelain veneers. Journal of Adhesive Dentistry, 6(1), 65–76.
- Magne, P., & Belser, U. (2002). Bonded Porcelain Restorations in the Anterior Dentition: A Biomimetic Approach. Quintessence Publishing.
- Pashley, D. H. (1996). Dynamics of the pulpo-dentin complex. Critical Reviews in Oral Biology & Medicine, 7(2), 104–133.
- Van Meerbeek, B., et al. (2011). State of the art of self-etch adhesives. Dental Materials, 27(1), 17–28.
- Brentel, A. S., et al. (2007). Microtensile bond strength of a resin cement to feldspathic ceramic after different etching and silanization regimens in dry and aged conditions. Dental Materials, 23(11), 1323–1331.
- Ivoclar. IPS Ceramic Etching Gel: Instructions for Use (etching times for IPS e.max Press and IPS e.max CAD: 20 s).
Last updated: · Editor contact: [email protected] · ulubeydental.com/contact-us